Welcome to my blog! My name is Gabriella Rivera, and I am pursuing a Master of Public Policy degree from the University of New Mexico. I have also been a policy assistant and office administrator for the health policy advocacy organization Health Action New Mexico for a little over a year. With this combination, both my academic and my professional work focus on health policy issues at the state level. Please follow to stay updated on health policy updates and please feel free to reach out with any questions.
Lowering the costs of prescription drugs
Prescription drug prices in the United States are about 2-6 times higher than in other high income countries, causing serious affordability and access issues including skipped doses and unfilled prescriptions. High prices also cause insurance companies to raise premium prices to cover their own costs. Here’s why the US drug industry needs fundamental reform.
“What [the drug companies] are doing to Americans is price-gouging us and they are holding us hostage. And people are dying. People are being forced to go to emergency rooms. People are having their legs amputated. They are going blind. They are having heart disease, liver damage. When does it stop?”
-Quinn Nystrom, Diabetes Activist
Virtually any drug you are prescribed in the U.S., chances are, you’re paying more for it than you would any other country. If this frustrates you, you’re not alone. Profiteering in the U.S. drug market is becoming a top issue for the American public, but meaningful reform remains elusive and complicated by decades of work in the opposite direction. There are three main reasons that the U.S. pharmaceutical market is failing its consumers.
First, the government is prohibited by law from negotiating directly with the manufacturers. Instead, insurance companies contract with private pharmacy-benefit managers (PBMs) to negotiate prices on their behalf. PBMs collect their own high fees for their services and strike exclusivity deals with the pharmaceutical companies, which discourages the production of generics.
Second, there is a concerning lack of competition for many drugs. Most major drugs have only one or two manufacturers producing a product, allowing those companies to charge exorbitant prices. Why? PBMs and manufacturers strike under-the-table exclusivity deals, making it so that patients and insurers don’t get the choice between different companies and prices.
Third, there is an egregious lack of transparency in the industry. Manufacturing and research costs, clinical success, PBM negotiations, and other expenses like advertising and marketing all remain behind closed doors. This makes it difficult for insurance companies, the government, or consumers to understand the real cost or merit of a drug, and results in an inability to regulate.
The resulting status quo for the pharmaceutical industry is a complex system with very little oversight or regulation. The powerful lobbying capacity of the pharmaceutical industry has created fear that regulation will stifle innovation and diminish the incentive to research and produce new drugs. However, as more consumers become aware of the price exploitation taking place in the industry, the possibility of meaningful reform becomes more of a reality.
Policy Proposals to Lower Drug Prices
Drug Importation: The Trump Administration recently enacted a policy to allow states to pass legislation to import certain drugs from Canada. This concept could also be implemented on a federal scale in conjunction with other policies, and federal guidelines could loosen to allow importation from more countries.
Feasible? Yes. Effective? Not really. Experts agree that this is a bandaid on a much bigger problem. The potential benefit to price levels would be dampened by the costs of importation. There would also be significant start-up costs to creating an infrastructure to ensure the quality of imported drugs.
Value-Based System: This is a system that sets prices based on risk, benefit, and effectiveness of each drug entering the market–basically a “grading” system to determine a fair price. A value-based pricing system would have to begin with transparency measures, so that the government and the public can better understand the true costs of producing a drug. This understanding would serve as a basis for the government to set price ceilings via a review board.
A value-based system could prove very difficult to navigate politically, however. Congress is hesitant to introduce transparency measures because the pharmaceutical companies target lobbying efforts against them. This would also be a complex system to implement, most likely with significant start-up costs.
Direct Government Negotiation: With this system, the government would look at two factors: a value based price and an international index, which averages the prices a drug is sold for in other countries. They would then directly negotiate with the drug manufacturer to set a price ceiling, above which they would incur a penalty. Any price increases would be reviewed.
However, this option would likely be even more difficult to accomplish politically. Although there is public support for regulations, Congress is unlikely to pass a sweeping reform to the system due to heavy pressure from the pharmaceutical lobby. This would also involve significant start-up costs, as well as more money and infrastructure to maintain a review board to constantly review and negotiate for more affordable drugs.
Shorter exclusivity periods: This would allow more competition in a quicker timeframe once a drug is introduced. Most drugs have an exclusivity period of 5 or 7 years, after which a generic can be produced. Reducing this period to 3 years would allow generics to be produced earlier, incentivizing lower prices because of competition.
However, this would only apply to new drugs, and few generics are produced even after the waiting period under the current system. Shortening these exclusivity periods would also be difficult politically as the manufacturers lobby heavily against it, but it would likely be more palatable than more sweeping reform like direct negotiation or pricing systems. It would be simple, easy and cheap to implement, and more feasible than other options, but would not have a profound effect in isolation.
Recommendation
Here’s what I believe we need in order to make real changes to the industry: A system of direct government negotiation, using value-based pricing and an international pricing index, combined with a shorter exclusivity period.
In combination, these policies would incentivize competition and transparency while preserving the incentive to innovate. Getting these policies passed will be difficult politically, but the issue is salient enough to garner public support, and state action on the issue will serve as important models to spur action on the federal level.
Reducing the Uninsured Rate in New Mexico
190,000 New Mexicans, 9% of the state population, have no form of health insurance.
Federal reform from the ACA halved New Mexico’s uninsured rate from 18% to 9% from 2013 to 2016. However, in 2017 the rate stagnated, and in 2018 there was a slight rise in the percentage of uninsured. New Mexico needs comprehensive, sustainable, state-level reform to retain the impact of the ACA and further reduce the uninsured rate.
Who are the uninsured?
The chart below shows the composition of those without health inurance in New Mexico. About 45% are Medicaid-eligible and 13% are eligible for federal marketplace subsidies. This means over half of the uninsured are eligible for free or subsidized coverage but are not utilizing it. The other 42% are ineligible for Marketplace subsidies. The rest are facing other accessibility or affordability issues. Research shows only 2% of those without insurance do not want coverage. How can New Mexico reach the 98% who want coverage but don’t have it?
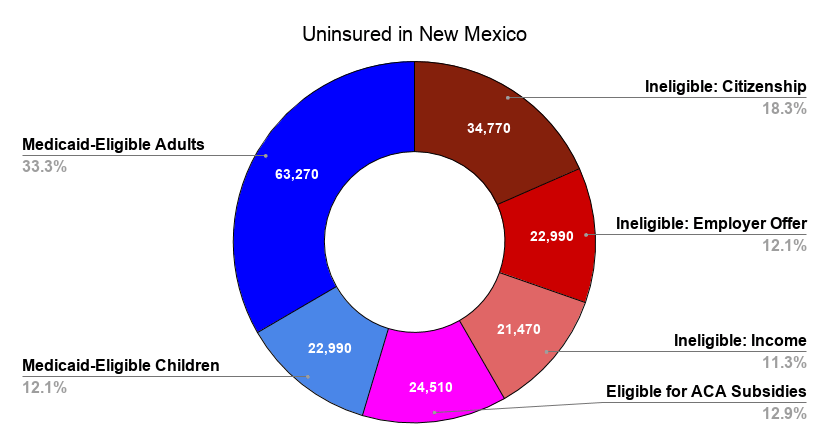
Comprehensive state reform: 3 integrated policies.
After reviewing policy options from around the country, my recommendation for New Mexico is to adopt a 3-part reform over the next few years.
The first component is a Targeted Medicaid Buy-In. This would make Medicaid available for purchase to those who do not qualify for Medicare, Medicaid, or federal subsidies for private coverage. This option would sell Medicaid coverage at cost, and the state can decide to subsidize this as much or as little as desired, by sliding scale or a fixed amount. If priced correctly, this could provide a source of affordable, comprehensive coverage for those who lack accessibility to the Marketplace. Governor Lujan Grisham has explicitly mentioned a Medicaid buy-in within her plan to reform health insurance, and the state legislature funded a study of four versions of the buy-in, concluding that this one was the best first step.
The second component is Medicaid auto-enrollment. This can be modeled three ways. SNAP-based, tax-based, or a combination of both. The SNAP-based option is modeled after a Louisiana program that streamlines Medicaid enrollment for children through SNAP benefits. Applying it to adults, it would work like this: if an individual has SNAP and is not insured, they would be sent a Medicaid card. They would technically be enrolled and consent to that enrollment the first time they use the card, and would then be able to opt-in or opt-out for the following year. The tax-based option would involve a check box on the NM income tax form asking for affirmative consent to use the information on the form to check for Medicaid eligibility, and if eligible, sign them up automatically. A combination of these two would comprehensively capture the Medicaid-eligible population and help with retention. The tax-based idea has already been considered as a part of a proposal in New Mexico, which is the next component of my recommendation.
The final component is the Shared Responsibility Requirement with Down Payment and Auto Enrollment options. Under this policy, individuals would be mandated to maintain insurance, similar to one of the original (since removed) components of the Affordable Care Act. The difference is that with this policy, if an individual has not maintained insurance and is subject to the financial penalty, they would get the option to use the money as a down payment for insurance for the following year. If they opt-in to this, they have two weeks to pick a plan. If they do not pick a plan within the two weeks, they will be automatically enrolled in the highest value plan that is covered entirely by their down payment and any federal subsidies they qualify for. BeWellNM, the state’s Marketplace exchange for private health coverage, created a task force to study this option in 2018. A bill was drafted but was pulled by the task force before committee, citing the need for more research about the interactions between agencies this option would necessitate. Advocates are planning on studying the option in depth for legislation in the 2021 session.
Combined, these policies would capture all uninsured populations and do so in a comprehensive, low risk manner. Advocates would have a lot of work on their hands though; the Shared Responsibility and Medicaid auto-enrollment particularly come with administrative difficulties and uncertain political feasibility. A successful campaign would engage all involved entities for these plans, including providers, insurance carriers, beWellNM, NM Tax and Revenue, and the uninsured themselves to contribute meaningful input and elicit support. The policies are likely to face resistance from some of these groups, as well as from other entities that traditionally oppose healthcare reform. However, the payoff could be massive if these plans are implemented. Not only would the state be considered a leader in healthcare reform, but it would sustainably and significantly reduce the uninsured rate in New Mexico, improving the health and lives of our workforce, our families, and our communities.

